A collaborative analysis of more than 844,000 adults from China, the United Kingdom, the United States and Spain confirms that the obesity classification framework proposed by a 2025 Lancet Commission improves detection of excess adiposity and clarifies its health consequences.
Beyond BMI: How the new definition changes prevalence estimates
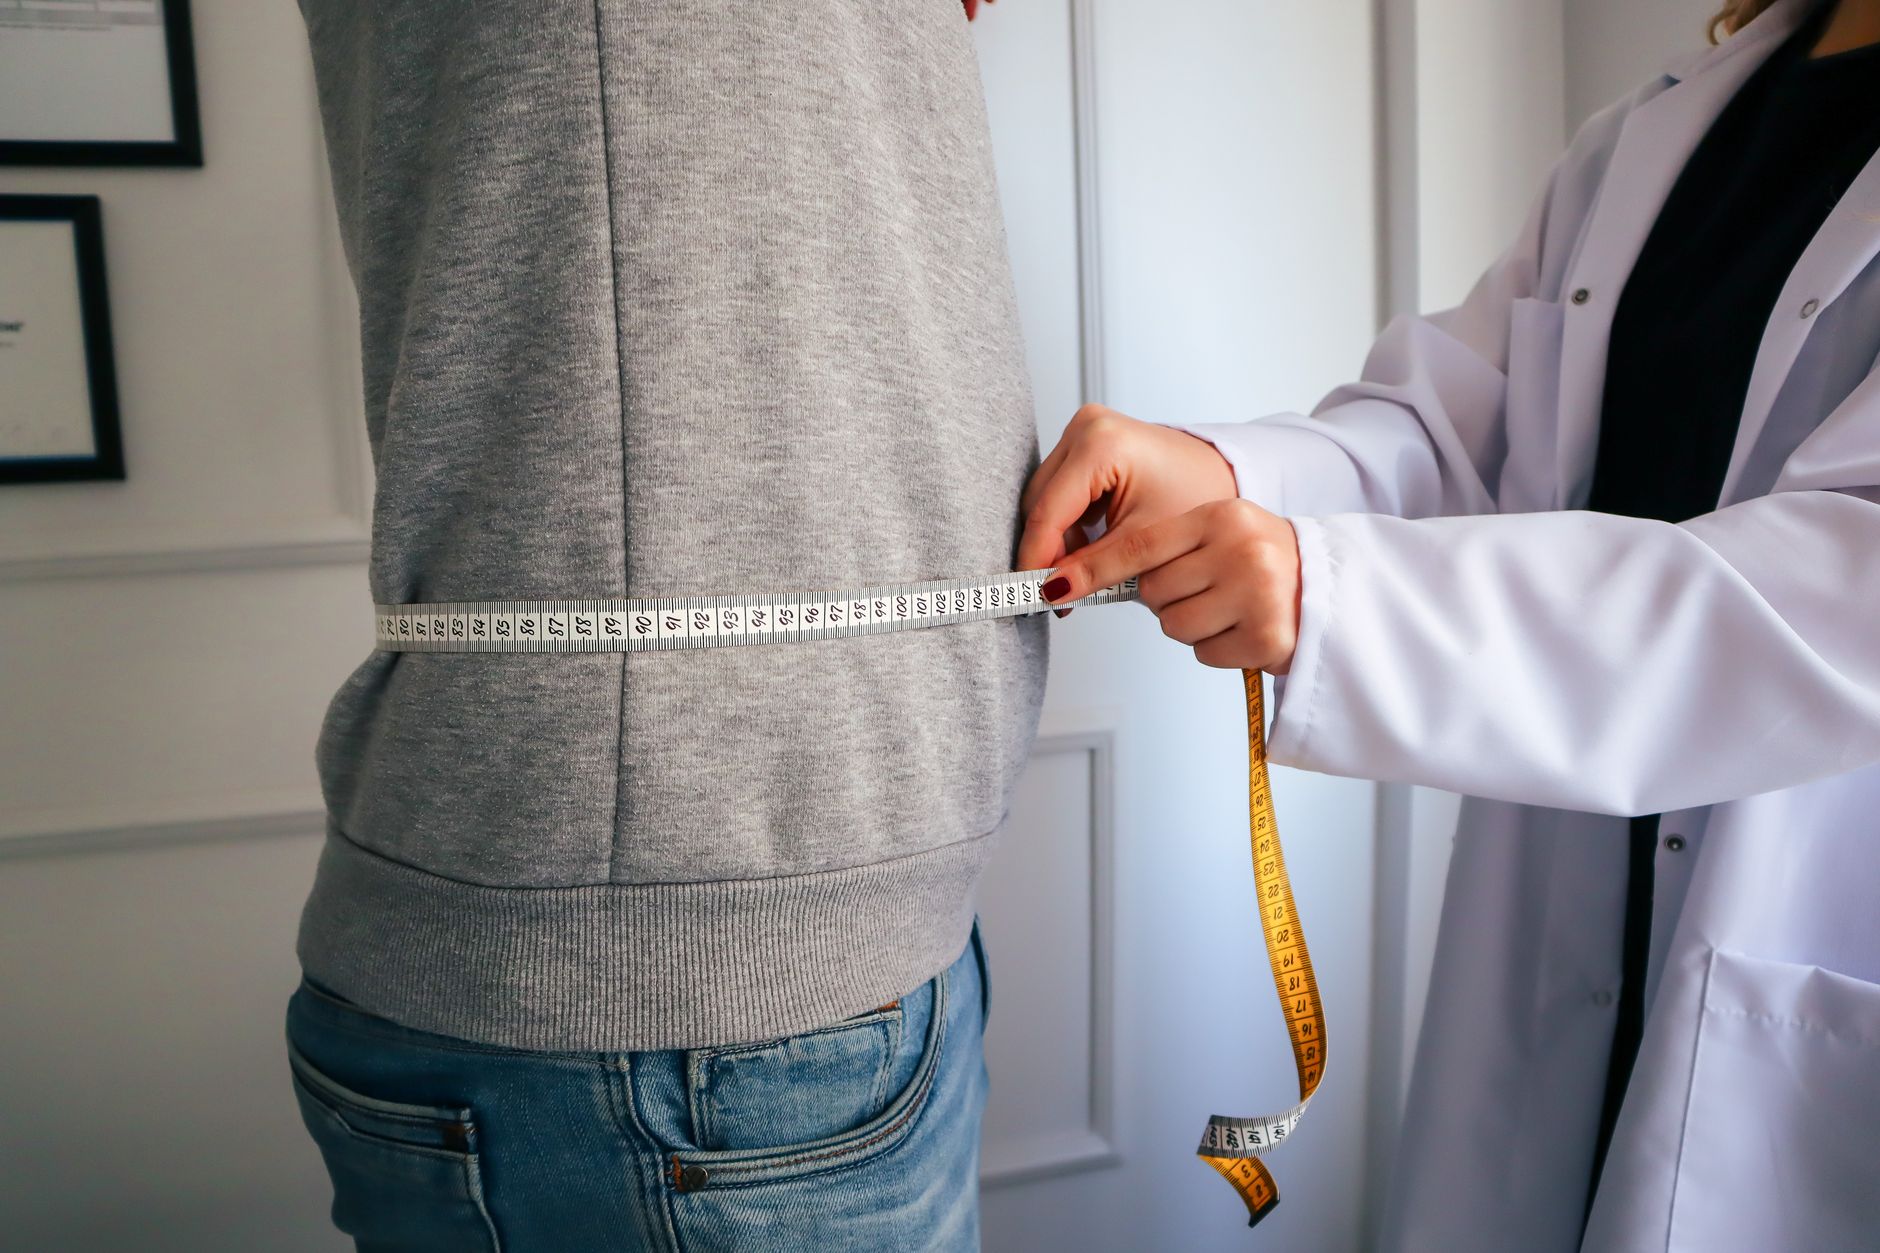
The Lancet Commission recommended distinguishing “clinical obesity”—excess fat that impairs organ function—from “preclinical obesity,” where excess fat is present but organ function remains intact. The commission also urged clinicians to supplement body‑mass index (BMI) with waist circumference (WC) and waist‑to‑height ratio (WHtR). Researchers applied this combined anthropometric definition (CAD‑obesity) to four large cohorts: the Kailuan Study in China (137,795 participants), the UK Biobank (436,203), the All of Us Research Program in the United States (218,841) and the SIDIAP database in Spain (51,269).
When obesity was defined by BMI alone, the authors found both over‑ and under‑identification. Across the four cohorts, BMI alone overestimated obesity in 1.2 % to 3.1 % of participants and underestimated it in 5.2 % to 8.6 %. Incorporating WC and WHtR raised overall obesity prevalence by 3.3 % to 7.4 % relative to BMI‑only estimates. Net increases were modest: 3.5 % in China, 3.3 % in the UK, 5.6 % in the US and 7.4 % in Spain.
Clinical versus preclinical obesity and long‑term outcomes
Within the CAD‑obesity group, clinical obesity was identified when at least one of 18 organ‑dysfunction criteria—ranging from heart failure and hypertension to obstructive sleep apnoea and chronic kidney disease—was present. To avoid attributing unrelated disease to excess fat, the investigators applied an attributable‑fraction (AF) approach, using cohort‑specific hazard ratios for incident organ dysfunction (HRs 1.62–2.07). The resulting AF values (0.38–0.52) adjusted the crude prevalence of organ dysfunction, which varied from 56.7 % in the US cohort to 75.3 % in the UK cohort.
After AF adjustment, clinical obesity comprised 22.7 % to 31.3 % of total obesity across the four populations, translating to an overall population prevalence of 5.6 % to 10.9 %. The majority of individuals classified as having preclinical obesity at baseline (77.4 % to 91.3 %) did not progress to clinical obesity over a ten‑year follow‑up period.
Mortality risk linked to the new classification
When mortality was examined, CAD‑obesity was associated with a higher risk of death, whereas obesity defined by BMI alone showed no significant mortality signal. Clinical obesity carried a hazard ratio of 1.69 (95 % CI 1.64–1.73) for all‑cause mortality, indicating a 69 % higher risk compared with non‑obese participants. Preclinical obesity conferred a more modest increase (HR 1.19, 95 % CI 1.14–1.24).
These findings support the Lancet Commission’s recommendation to adopt a multi‑measure diagnostic framework for obesity. By capturing individuals whose excess adiposity is already affecting organ systems, the approach may enable more precise risk stratification, targeted interventions and better allocation of healthcare resources worldwide.

Steve Lopez is a Senior Editorial Columnist and Health & Public Policy reporter for News Raise. Steve focuses on healthcare advancements, medical technologies, and public health policies.